

Zirconia vs emax is the most common material question we get, and it is usually asked as a strength question when it is really a translucency and space question. Both materials survive at rates that make strength a poor tiebreaker on most single units. What separates them is what the tooth looks like underneath, how much room you have taken, and where the restoration sits in the mouth.
Here is how we decide when a prescription leaves it to us, and what to tell us if you want to decide it yourself. The product pages sit at zirconia crowns and emax crowns.
What the survival data actually shows
Start here, because it removes the argument most people expect to have. Systematic review data on monolithic single crowns puts 5 year survival at 98.5 percent for monolithic lithium disilicate and 96.8 percent for monolithic densely sintered zirconia. Separate work on lithium disilicate single crowns reports 100 percent cumulative survival at 2 years and 97.8 percent at 5 years. Both materials reach 5 year survival comparable to metal ceramic.
Two things follow from that. The first is that on a single unit in a normal mouth, either material will almost certainly still be there in five years, so choosing on survival alone is choosing on a difference of under two percentage points. The second is that monolithic beats layered on both materials. The reviews are consistent that monolithic lithium disilicate and monolithic zirconia show significantly fewer ceramic fractures and less chipping than veneered alternatives, because the failure mode you are avoiding is the porcelain shearing off the core rather than the core breaking.

Strength matters less often than it gets used
Most of the time zirconia vs emax is decided before strength enters the conversation at all, which is why the sections below spend more time on translucency, stump colour and reduction than on flexural figures.
Zirconia is substantially stronger and that is not in dispute. The question is whether the extra strength is doing anything on the case in front of you. On a single posterior unit with adequate occlusal reduction and no parafunction, lithium disilicate is not the weak option. It is a material with 98.5 percent 5 year survival.
Where the strength genuinely decides it is at the margins of the indication. Long span bridges. Second molars in a heavy bruxer. Cases where you could not take the reduction you wanted and the restoration will be thin. Cantilevers. In those situations the extra strength is not a luxury and zirconia is the answer, which is also why our zirconia bridges line exists as a separate product.
There is a middle material worth knowing about. Zirconia reinforced lithium silicate sits between the two, with reported flexural strength around 210 to 370 MPa. It is a reasonable answer where you want glass ceramic esthetics with a little more margin for error, and it is worth asking about rather than assuming the choice is binary.
Translucency, and why zirconia still loses in the anterior
This is the real dividing line. Higher crystalline content is what makes zirconia strong and it is also what makes it opaque. Translucent grades have narrowed the gap and have not closed it. The literature still describes high translucency zirconia as comparatively opaque against lithium disilicate, which is why monolithic zirconia remains primarily a posterior material.
In practice that means a single central incisor next to a natural tooth is the hardest case in dentistry and lithium disilicate gives us more to work with. Zirconia can be layered to get there, and layering reintroduces the chipping risk the monolithic data warns about. On an anterior case we would rather have a material that looks right monolithically than a stronger one that needs veneering to look acceptable.
The exception runs the other way. Where the preparation is dark, from a metal post, a titanium abutment, or a heavily discoloured tooth, translucency stops being an advantage and becomes a problem. A translucent crown over a dark stump shows the stump. That is a case for opacity, and zirconia is the material that provides it.
Preparation is the part you control
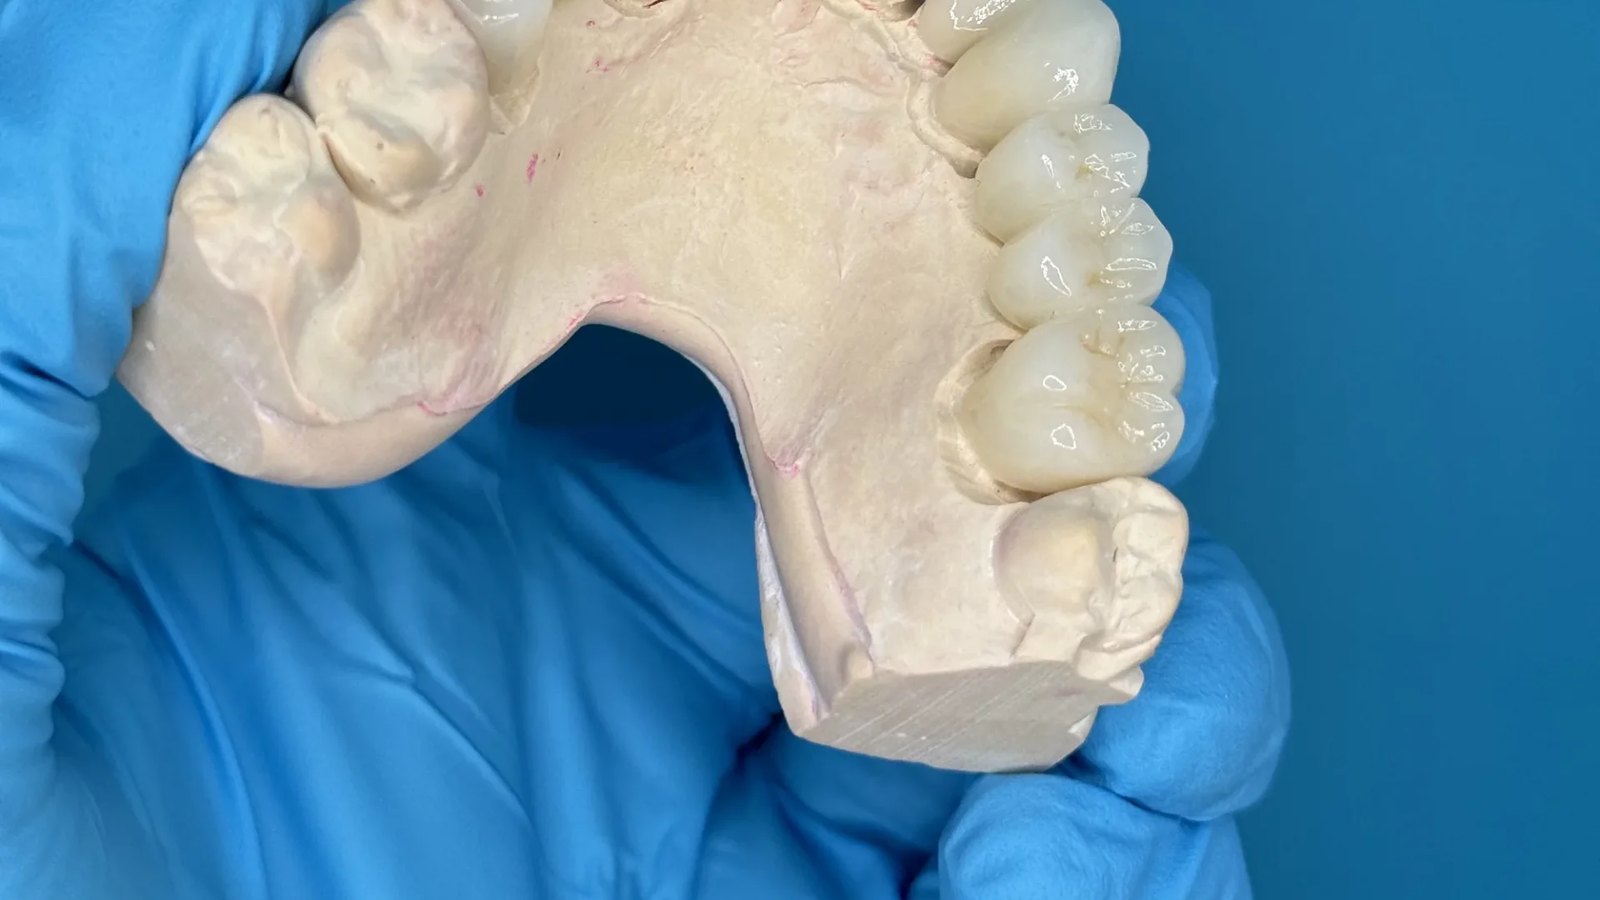
The material choice is often made for us by the reduction, and by the time the case reaches the bench that decision is already fixed. This is the single most useful thing a prescription can get right.
- Tell us the reduction you achieved rather than the one you planned. If occlusal clearance is tight we will tell you which material still works in that thickness.
- Send the stump shade. Not the target shade, the shade of the prepared tooth. On a translucent material it changes the final result more than the shade tab does.
- Say whether the tooth is vital, post retained or heavily discoloured, because each of those pushes the answer toward opacity.
- Flag parafunction. A bruxism history is the fastest route from a reasonable lithium disilicate case to a zirconia one, and it is also a reason to discuss an occlusal guard alongside the restoration.
- Mark the margin clearly. Both materials want a defined margin and neither forgives a guess.
Bonding, and the difference that survives to the chair
Lithium disilicate etches with hydrofluoric acid and bonds adhesively, which is part of why it performs well in thin sections. The restoration and the tooth end up working as a unit. Zirconia does not etch the same way and is conventionally cemented or bonded with a phosphate monomer primer, which is the same chemistry discussed in our note on titanium base bonding.
The practical consequence is that a thin lithium disilicate restoration relies on the bond and a zirconia one relies on its own bulk. If the case will be cemented rather than bonded, that pushes the answer toward zirconia. On implant work the retention route matters as much as the material, which is covered in screw retained versus cement retained.
What actually fails, and what that tells you
Worth knowing what you are protecting against, because the two materials fail differently and the studies point the same way on both. The dominant failure in veneered restorations is the porcelain chipping or shearing away from the core rather than the core itself breaking. That is why the review evidence favours monolithic designs in both materials, and it is why a layered zirconia anterior crown carries a risk that a monolithic lithium disilicate one does not.
When a monolithic restoration does fail it tends to fail properly, as a bulk fracture rather than a chip, and a bulk fracture is a remake rather than a repair. That is not an argument against monolithic. It is an argument for getting the reduction and the material right first time, because neither material offers you a cheap intermediate repair the way a metal ceramic crown sometimes does.
The other thing we see come back is a colour failure rather than a mechanical one, and it is almost always a translucent restoration over a stump we were not told about. That is a communication failure rather than a material one, and it is entirely preventable at the prescription stage.
The code is the same, which surprises people
Both materials are reported under D2740, crown porcelain or ceramic substrate. There is no separate code for zirconia and no separate code for lithium disilicate, which is why both of our product pages carry the same code in the title. The material difference sits in the laboratory fee rather than the procedure code.
For comparison, a metal ceramic crown runs under D2750, D2751 or D2752 depending on the alloy tier, which is set out on our PFM crowns page. Recementation is D2920. An implant supported ceramic crown is D6065 rather than D2740, and the abutment beneath it codes separately as covered in custom versus stock abutment. Reference values only, so confirm against current CDT.
How we settle zirconia vs emax when you leave it to us
- Anterior single unit, vital tooth, good reduction. Lithium disilicate, almost always. Esthetics is the job and the survival data does not penalise it.
- Anterior over a dark stump or a titanium abutment. Zirconia, for opacity, and we will discuss whether it needs surface characterisation.
- Posterior single unit, normal function. Either works. We default to monolithic zirconia for the margin of safety unless esthetics is unusually demanding.
- Posterior with limited clearance. Zirconia, because it holds up thinner.
- Any bruxer. Monolithic zirconia, and a guard.
- Bridges beyond three units, or any cantilever. Zirconia.
- Implant crowns. Depends on the abutment and the retention route more than on the material. See implant crowns.
If you want the decision made case by case rather than by rule, say so on the prescription and we will call. Case planning is on for dentists, scanning is on intraoral scanners, and the full line sits under crowns and bridges.
Questions from the prep
Is zirconia always stronger than emax?
Yes as a material property, and that is not the same as saying it lasts longer in the mouth. The 5 year survival figures are 96.8 percent for monolithic zirconia against 98.5 percent for monolithic lithium disilicate. Strength decides the hard cases, not the average one.
Can zirconia be used in the anterior?
Yes, and it is done constantly. The question is whether it needs layering to look right, because layered restorations chip more than monolithic ones. Where the case is esthetically demanding and the stump is not dark, lithium disilicate is the easier route to a good result.
Which one can be adjusted chairside?
Both, carefully, with the right burs and water. Zirconia needs polishing rather than glazing after adjustment, and an unpolished adjusted zirconia surface is abrasive to the opposing dentition. If you adjust either material at delivery, polish it properly.
Does the stump shade really matter that much?
On lithium disilicate, yes, more than almost anything else you send. The material is translucent by design, so what is underneath shows through. Send the stump shade and a photograph if the tooth is discoloured.
What about a case where I cannot decide?
Send it with the stump shade, the reduction and a note about function, and ask us. We would rather spend five minutes on the phone than remake an anterior case that came back for the right reason.
Material selection
Not sure which material the case wants
Send the stump shade, the clearance and any parafunction history and we will recommend a material and say why. No charge for the planning call.
Written by Amanda Elder, Lab Manager at International Dental Arts. IDA has been a family founded dental laboratory in Tulsa since 1984, working with independent practices across the country. If you want a case reviewed before you commit, get in touch.


